

HIV: Infection Control/Exposure Control Issues for Oral Healthcare Personnel
Course Number: 97
Course Contents
Clinical Manifestations
Available scientific evidence suggests a dynamic process in which initial and ongoing immunological responses to HIV infection are not only unsuccessful in clearing HIV but, paradoxically, they are paralleled by a progressive reduction in immunocompetence.7 Individual variations exist, but a pattern of disease progression has been established as consisting of three phases: (1) primary infection, (2) a period of clinical latency, and, finally, (3) clinically apparent disease.8

After an incubation period of 1 to 3 weeks, 50% to 70% of patients experience an ill-defined acute retro-viral syndrome characterized by mononucleosis-like symptoms of fever, lethargy, malaise, sore throat, arthralgia, myalgia, headaches, photophobia, maculopapular rash, and lymphadenopathy.7,8 During clinical latency (8 to 24 months), the patient is free of overt signs and symptoms. From these, patients may progress in one of three ways: typical progressors, rapid progressors and long-term non-progressors.8 Without appropriate antiretroviral therapy an HIV-infected patient will progress to AIDS and is at risk of developing a multitude of opportunistic infections, the most common of which are summarized in Table 1.9
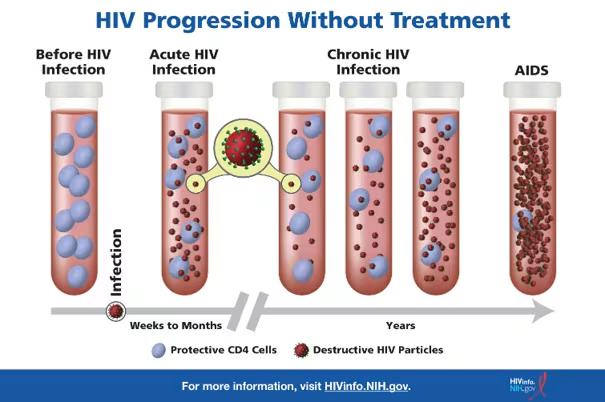
Table 1. Opportunistic illnesses (AIDS-defining conditions).9
|
| * Only among children aged <6 years † Only among adults, adolescents, and children aged ≥6 years § Suggested diagnostic criteria for these illnesses, which might be particularly important for HIV encephalopathy and HIV wasting syndrome, are described in the following historical references: CDC. 1994 Revised classification system for human immunodeficiency virus infection in children less than 13 years of age. MMWR 1994;43(No. RR-12). CDC. 1993 Revised classification system for HIV infection and expanded surveillance case definition for AIDS among adolescents and adults. MMWR 1992;41(No. RR-17). |
HIV-induced immunosuppression places the patient at risk for numerous oral conditions (Table 2). The most notable are erythematous or pseudomembranous candidiasis, hairy leukoplakia, Kaposi’s sarcoma, non-Hodgkin’s lymphoma, linear gingival erythema and periodontal diseases including (necrotizing ulcerative periodontitis).10-11 Hairy leukoplakia and oral candidiasis are positive predictors of HIV disease progression. Contemporary antiretroviral therapy significantly decreases this risk.12 Therefore, for a patient on an antiretroviral regimen, the development of an HIV-associated oral manifestation may signal therapeutic failure.11 If this occurs, the patient should be promptly referred to their managing healthcare professional for evaluation.

Kaposi's Sarcoma

Hairy Leukoplakia

Oral Candidiasis
| Group 1 Lesions strongly associated with HIV infection | Candidiasis Erythematous Pseudomembraneous Hairy leukoplakia Kaposi’s sarcoma Non-Hodgkin’s lymphoma Periodontal disease Linear gingival erythema Necrotizing (ulcerative) gingivitis Necrotizing (ulcerative) periodontitis |
| Group 2 Lesions less commonly associated with HIV infection | Bacterial infections Mycobacterium avium-intracellularae Mycobacterium tuberculosis Melanotic hyperpigmentation Necrotizing (ulcerative) stomatitis Salivary gland disease Dry mouth due to decreased salivary flow rate Swelling of major salivary glands Thrombocytopenia purpura Ulceration NOS (not otherwise specified) Viral infections Herpes simplex virus Human papillomavirus (warty-like) lesions Condyloma acuminatum Focal epithelial hyperplasia Verruca vulgaris Varicella-zoster virus Herpes zoster Varicella |
| Group 3 Lesions seen in HIV infection | Bacterial Actinomyces israelii Escherichia coli Klebsiella pneumonia Cat-scratch disease Drug reactions (ulcerative, erythema multiforme, lichenoid, toxic epidermolysis) Epithelioid (bacillary) angiomatosis Fungal infection other than candidiasis Cryptococcus neoformans Geotrichum candidum Histoplasma capsulatum Mucoraceae (mucormycosis zygomycosis) Aspergillus flavus Neurological disturbances Facial palsy Trigeminal neuralgia Recurrent aphthous stomatitis Viral infections Cytomegalovirus Molluscum contagiosum |