HIV: Infection Control/Exposure Control Issues for Oral Healthcare Personnel
Course Number: 97
Course Contents
Etiology and Epidemiology
The first cases of acquired immunodeficiency syndrome (AIDS) in the United States were reported in 1981.2 Soon thereafter, HIV, which is an RNA virus of the Retroviridae family, was identified as the underlying pathogen. HIV probably entered the human population by cross-species transmission of the ancestral virus found in wild chimpanzees in Central Africa. The spread of HIV in Africa corresponds to urbanization and occurred before the recognition of AIDS.3
HIV is a bloodborne pathogen acquired in non-occupational settings most readily either across mucous membranes or parenterally by 5 prime modes of transmission:4
unprotected anal sex
unprotected vaginal sex
mother to child spread during pregnancy, delivery, or breast feeding
sharing needles during injection drug use
sharing needles, syringes, or other drug injection equipment
The estimated per exposure risk of HIV transmission following (1) receptive anal intercourse is 1 to 30%; (2) insertive anal or receptive vaginal intercourse it is 0.1 to 10%; (3) insertive vaginal intercourse it is 0.1 to 1%; and (4) injection drug use with needle sharing it is 0.67% per needle-sharing contact.5 The risk increases with advanced HIV disease, cervical or anal dysplasia, circumcision status, and the presence of genital ulcer disease. Data are lacking on oral sex transmission of HIV, but cases exist where oral sex was the only risk factor.5
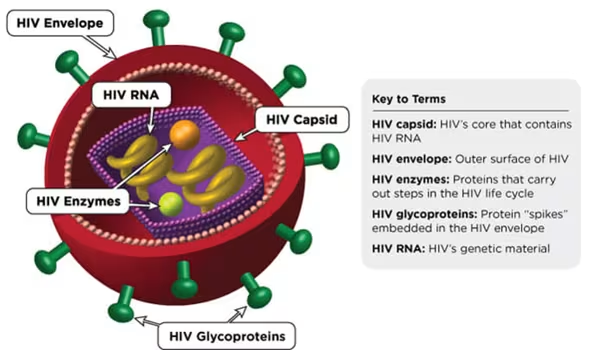
HIV has the same general life cycle as other viruses. Infection begins when a virion attaches to a host cell. CCR5 and CXCR4 are the two major co-receptors used by HIV-1. The viral strains can be classified by which co-receptor they use: CCR5-tropic, CXCR4-tropic, or mixed-tropic. CCR5-tropic strains predominate during early stages of infection and remain dominant in 50-60% of late stage disease.<sup>[6](/en-us/ce-courses/ce97/references#6)</sup> Capsid- or envelop-related viral proteins mediate attachment.
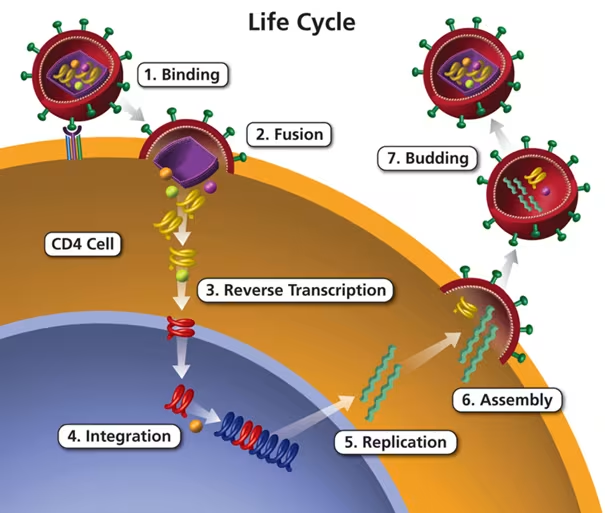
These are 7 stages in the life cycle of the HIV virus. Stage 1 involves HIV binding to the surface of the CD4 host cell. Viral entry into the host cell is mediated by other viral proteins which promote the second stage, fusion to the host cell membrane. Once the virus has gained entry into the host cell, it loses its capsid proteins by the process known as uncoating. Since HIV is an RNA retrovirus, uncoating is followed by stage 3 reverse transcription. During this stage, the viral RNA is first copied into DNA and then transcribed into a mRNA which allows it to penetrate the host cell nucleus. Once in the nucleus, stage 4 is the integration of HIV into the host cell DNA. The viral nucleic acid now becomes available for stage 5, replication, which requires the generation of protein kinase-dependent nucleoside triphosphates (ribo- or deoxyribo-) to be incorporated into the new viral genome by viral or host cell polymerases. During stage 6, the newly synthesized mRNA is translocated to host cell ribosomes. Viral proteins are then assembled with the duplicate viral genome and begin the process of maturation. Maturation, characterized by cleavage of viral proteins by proteases, is essential for the newly formed virion to become infectious. Following maturation, viruses egress from the host cell in the final stage of the life cycle either by cell lysis or budding through the cell membrane.